





Agentic AI & Inbound Call Automation Solution for a Multi-Specialty Medical Practice
A multi-specialty practice was handling 300+ inbound calls per day entirely through live front desk staff. Every call, regardless of complexity, required a human to answer it. Intuz built a modular AI voice agent covering four departments that automated 85% of call volume within 30 days, without adding headcount.

Core Back Office Challenges
Before Automation
“The practice needed a system, not more staff. Something that could handle the predictable 85% so the team could focus on work that actually requires human judgment.”
Patients abandoning calls at peak hours
There was no way to prioritize urgent clinical needs over routine requests. Every caller waited in the same queue, and during peak hours patients were hanging up before anyone answered.
70%+ of staff time spent on repetitive calls
Appointment confirmations, eligibility checks, refill requests, and billing status inquiries were consuming the majority of trained staff hours every single day. Predictable, low-complexity calls were crowding out work that required human judgment.
Inconsistent data capture causing downstream errors
Different staff members collected different information for the same call types. That inconsistency led to scheduling mistakes, missed follow-ups, and errors that compounded through the system.
No structured escalation for clinical urgency
Patients describing symptoms or medication emergencies were triaged by whoever happened to answer. There was no detection logic, no guaranteed handoff to clinical staff when it mattered most.
Solution Planning and Agentic
System Architecture
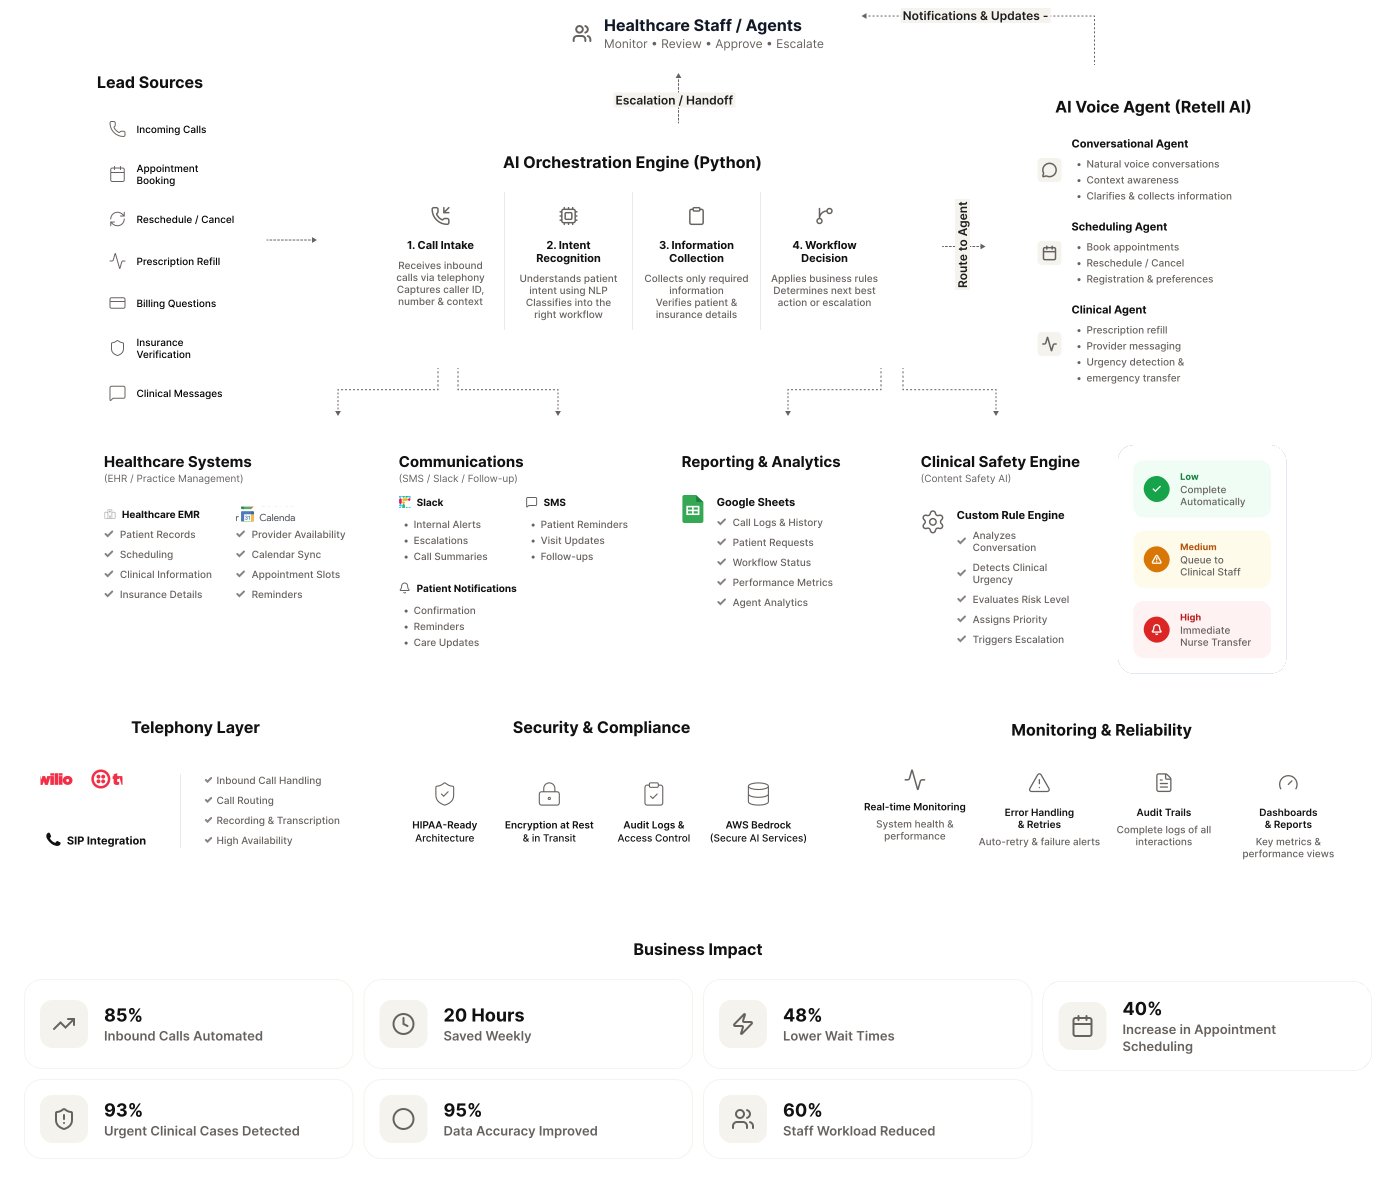
Natural language call routing
Callers describe what they need in their own words. The agent interprets intent, clarifies when needed, and routes with full context carried forward. No phone trees, no menu navigation.
Appointment scheduling and patient registration in one flow
Identity, insurance, preferences, and visit reason captured once. Registration data auto-populates into scheduling without re-prompting the caller at any stage.
Clinical urgency detection
Escalation logic trained on real-world phrasing, not keyword lists. The system detects emergencies from context and phrasing, including understated or ambiguous language, and routes to nursing staff immediately.
Full administrative coverage
Insurance inquiries, billing, referrals, lab tracking, fax follow-ups, and telemedicine handled through structured intake that ensures the right team gets complete context every time.
Automated post-call summaries
Formatted records including intent, patient ID, urgency flags, and message details are delivered to Gmail and Google Sheets within minutes of every call. Zero manual note-taking required.
Mid-call intent shift handling
When a caller shifts from a billing question to a scheduling request mid-call, the system detects the change, transfers to the correct agent, and carries all captured data forward without re-identifying the patient.
Purpose-Built AI Agents for
Every Step of the Call
One modular system covering four departments.
Each agent built for a specific call type, escalation pattern, and data requirement.
Natural Language Call Routing
Callers describe what they need in plain language. The agent interprets intent without phone trees, clarifies when needed, and routes with full context carried forward to the next agent.
Appointment Scheduling and Patient Registration
Captures identity, insurance, preferences, and visit reason in a single flow. Registration data auto-populates into scheduling without asking the caller to repeat information.
Clinical Communication and Urgency Detection
Handles refills, provider messages, and pharmacy coordination. Detects clinical emergencies from context and phrasing, not just keywords, and routes to nursing staff immediately.
Insurance, Billing and Administrative Intake
Covers insurance inquiries, billing, referrals, lab tracking, and telemedicine. Structured intake ensures the right team receives complete context on every call.
Post-Call Summaries and Reporting
Formatted records delivered to Gmail and Google Sheets within minutes of every call. Intent, patient ID, urgency flags, and message details captured automatically with no manual note-taking.
Mid-Call Intent Shift Handling
When a caller changes what they need mid-call, the system detects the shift, transfers to the correct agent, and carries all captured data forward without re-identifying the patient.
Engineering Decisions
Decision 01
Four separate agents, not one monolithic system.
A single agent handling all call types would require one model to do too many jobs reliably. Building four purpose-specific agents meant each could be optimized for its own call patterns, escalation triggers, and data requirements without compromising the others.
Decision 02
Context carries forward across every agent transfer.
When a call shifts from one department to another, re-identifying the patient creates friction. Every transfer passes full call context including intent, patient ID, and captured data to the receiving agent so the caller never has to repeat themselves.
Decision 03
Urgency detection trained on real phrasing, not keywords.
Keyword-based escalation misses the way patients actually describe symptoms. Understated, vague, or buried in a routine call, these signals are invisible to a keyword list. The clinical urgency detection logic was trained on real-world phrasing patterns so the system catches what a keyword list would miss.
Decision 04
Launched in parallel with live agents, not as a hard cutover.
Going live alongside existing staff meant real calls were handled safely from day one while the team learned to work with AI summaries, escalation handling, and quality flagging. This reduced operational risk during the most critical phase of deployment.
How We Built It
Four Phases, One Seamless System
Each phase fed directly into the next. Discovery shaped the architecture, architecture shaped the agents,
agents were stress-tested before going live, and staff were trained before any hard cutover happened.
Phase 1
Discovery and Call Mapping
Every call type, escalation trigger, and routing rule was mapped through structured staff interviews before a single flow was built. This phase defined the decision logic the entire system runs on.
Phase 2
AI Architecture Design and Validation
Four-agent structure, decision logic, and transfer conditions were designed and stress-tested against real call patterns before development began. No assumptions carried into build.
Phase 3
Agent Development and Clinical Safety Testing
Each agent was built and tested independently, then integrated. Clinical escalation flows were verified against urgency scenarios including ambiguous language, understated symptoms, and mid-call intent shifts.
Phase 4
Parallel Launch and Staff Training
The system launched alongside live agents. Staff were trained on AI summaries, escalation handling, and quality flagging before any volume was handed over. No hard cutover, no operational risk.
End-to-End Workflow
Call comes in. Right team picks up.
Six steps in between.
One AI voice agent. Four departments. Every call routed, handled, and logged without a live agent touching the predictable 85%.
01
Patient calls in via Twilio or SIP.
The call is received and passed immediately to the AI voice agent. No hold queue for routine calls. No phone tree to navigate.
02
Agent detects intent from natural language.
The caller describes what they need. The agent interprets intent, asks one clarifying question if needed, and selects the correct department agent. No menus, no prompts.
03
Structured data captured in a single pass.
Identity, insurance, visit reason, and preferences collected once in a natural sequence. Only what is relevant to that call type is asked. No unnecessary questions, no repeated prompts.
04
Urgency detected and escalated if needed.
Clinical calls are assessed for urgency from context and phrasing, not keywords. If an emergency is detected, the call is routed to nursing staff immediately with full context attached.
05
Routine calls handled and closed by the agent.
Confirmations, eligibility checks, refill requests, billing status, and administrative inquiries resolved without involving a live staff member.
06
Post-call summary delivered automatically.
Intent, patient ID, urgency flags, and message details formatted and sent to Gmail and Google Sheets within minutes. Staff have complete records without touching a notepad.
Technical Challenges We Overcame
Building a voice agent for a clinical environment means the cost of a wrong routing decision is not a bad user experience.
It is a missed medical emergency. Several challenges required solutions that went beyond standard voice agent engineering.
Challenge 01
Callers who shift intent mid-call
A patient calling about billing might mention a symptom before hanging up. Standard routing locks the call into the first detected intent and loses everything after the transfer.
We built context-transfer logic that detects mid-call intent shifts, routes to the correct agent, and carries all captured data forward. The patient is never re-identified and no information is lost between agents.
Challenge 02
Urgency that does not sound urgent
Patients describing a medical emergency rarely use clinical language. “I’ve been feeling a bit off” can mean something serious. Keyword-based detection would miss it.
Escalation logic was trained on real-world phrasing patterns, not keyword lists. The system evaluates context, tone, and the combination of statements — achieving 93% accuracy in detecting urgent clinical cases from day one.
Challenge 03
Different call types needing different data without fatiguing the caller
Scheduling needs different information than a refill request, which needs different information than a billing inquiry. Asking all possible questions on every call creates friction and drop-off.
Each call type has its own structured intake sequence that collects only what is relevant, in a natural order. Callers are not over-questioned and never asked to repeat information already captured.
Challenge 04
Inconsistent data capture across call types
Before automation, different staff collected different information for identical call types. That inconsistency created scheduling errors and missed follow-ups downstream.
Structured intake templates enforce consistent data collection for every call type regardless of which agent handles it. The same fields, the same sequence, every time.
Challenge 05
Clinical safety during parallel launch
Going live while real calls were still being handled by staff meant errors could affect patients. A hard cutover was not an option.
The system launched in parallel with live agents. Escalation flows were verified against real urgency scenarios before any volume transferred. Staff were trained on AI summaries and flagging before the handover began.
Tools & technologies
Tools and Technologies We Used
Every tool was chosen for reliability in a live clinical environment where a routing error is not a UX problem. It is a patient safety risk.


